

 弊社は製品に自信を持っており、面倒な製品を提供していません。


本当質問と回答の練習モード
現代技術のおかげで、オンラインで学ぶことで人々はより広い範囲の知識(SEND有効な練習問題集)を知られるように、人々は電子機器の利便性に慣れてきました。このため、私たちはあなたの記憶能力を効果的かつ適切に高めるという目標をどのように達成するかに焦点を当てます。したがって、MRCPUK Certification SEND練習問題と答えが最も効果的です。あなたはこのEndocrinology and Diabetes (Specialty Certificate Examination)有用な試験参考書でコア知識を覚えていて、練習中にEndocrinology and Diabetes (Specialty Certificate Examination)試験の内容も熟知されます。これは時間を節約し、効率的です。
現代IT業界の急速な発展、より多くの労働者、卒業生やIT専攻の他の人々は、昇進や高給などのチャンスを増やすために、プロのSEND試験認定を受ける必要があります。 試験に合格させる高品質のEndocrinology and Diabetes (Specialty Certificate Examination)試験模擬pdf版があなたにとって最良の選択です。私たちのEndocrinology and Diabetes (Specialty Certificate Examination)テストトピック試験では、あなたは簡単にSEND試験に合格し、私たちのEndocrinology and Diabetes (Specialty Certificate Examination)試験資料から多くのメリットを享受します。
SEND試験学習資料の三つバージョンの便利性
私たちの候補者はほとんどがオフィスワーカーです。あなたはEndocrinology and Diabetes (Specialty Certificate Examination)試験の準備にあまり時間がかからないことを理解しています。したがって、異なるバージョンのSEND試験トピック問題をあなたに提供します。読んで簡単に印刷するには、PDFバージョンを選択して、メモを取るのは簡単です。 もしあなたがEndocrinology and Diabetes (Specialty Certificate Examination)の真のテスト環境に慣れるには、ソフト(PCテストエンジン)バージョンが最適です。そして最後のバージョン、SENDテストオンラインエンジンはどの電子機器でも使用でき、ほとんどの機能はソフトバージョンと同じです。Endocrinology and Diabetes (Specialty Certificate Examination)試験勉強練習の3つのバージョンの柔軟性と機動性により、いつでもどこでも候補者が学習できます。私たちの候補者にとって選択は自由でそれは時間のロースを減少します。
信頼できるアフターサービス
私たちのSEND試験学習資料で試験準備は簡単ですが、使用中に問題が発生する可能性があります。SEND pdf版問題集に関する問題がある場合は、私たちに電子メールを送って、私たちの助けを求めることができます。たあなたが新旧の顧客であっても、私たちはできるだけ早くお客様のお手伝いをさせて頂きます。候補者がEndocrinology and Diabetes (Specialty Certificate Examination)試験に合格する手助けをしている私たちのコミットメントは、当業界において大きな名声を獲得しています。一週24時間のサービスは弊社の態度を示しています。私たちは候補者の利益を考慮し、我々のSEND有用テスト参考書はあなたのSEND試験合格に最良の方法であることを保証します。
要するに、プロのSEND試験認定はあなた自身を計る最も効率的な方法であり、企業は教育の背景だけでなく、あなたの職業スキルによって従業員を採用することを指摘すると思います。世界中の技術革新によって、あなたをより強くする重要な方法はEndocrinology and Diabetes (Specialty Certificate Examination)試験認定を受けることです。だから、私たちの信頼できる高品質のMRCPUK Certification有効練習問題集を選ぶと、SEND試験に合格し、より明るい未来を受け入れるのを助けます。
MRCPUK SEND 試験シラバストピック:
| セクション | 比重 | 目標 |
|---|---|---|
| 生殖系およびその他の内分泌系疾患 | 15% | - 肥満および脂質代謝異常 - 内分泌性高血圧および稀な症候群 - 思春期の発達異常および性分化の障害 - 多嚢胞性卵巣症候群 |
| 下垂体・視床下部の疾患 | 15% | - 下垂体腺腫:プロラクチノーマ、先端巨大症、クッシング病 - 下垂体機能低下症とホルモン補充療法 - 尿崩症およびSIADH - 視床下部の機能障害 |
| 副腎・副甲状腺・代謝性骨疾患 | 15% | - クッシング症候群、アジソン病、褐色細胞腫 - 骨粗しょう症、骨軟化症、パジェット病 - 原発性・続発性アルドステロン症 - 副甲状腺機能亢進症、副甲状腺機能低下症 |
| 甲状腺の疾患 | 15% | - 甲状腺結節および甲状腺がん - 甲状腺炎および臨床的に顕在化しない機能異常 - 甲状腺機能亢進症:バセドウ病、結節性甲状腺機能亢進症 - 甲状腺機能低下症および粘液水腫性昏睡 |
| 糖尿病 | 40% | - 1型糖尿病
|
MRCPUK Endocrinology and Diabetes (Specialty Certificate Examination) 認定 SEND 試験問題:
A 19-year-old man was seen in the diabetes clinic. He had lost 2 kg in weight since the diagnosis of diabetes mellitus 18 months previously. At presentation, his body mass index was 33 kg/m2 (18-25), his random plasma glucose was 18.0 mmol/L and his haemoglobin A1c was 56 mmol/mol (20-42). He was taking gliclazide, and metformin had been added later. His father and grandfather had developed diabetes mellitus during their twenties.
Investigations:
haemoglobin A1c56 mmol/mol (20-42)
serum C-peptide301 pmol/L (180-360)
anti-glutamic acid decarboxylase (GAD)
antibodiesnegative
What is the most likely diagnosis?
- A. chronic pancreatitis
- B. type 2 diabetes mellitus
- C. latent-onset diabetes of autoimmunity
- D. type 1 diabetes mellitus
- E. maturity-onset diabetes of the young
正解:E 🗳️
A 34-year-old woman presented with palpitations, heat intolerance and a slight tremor. She was 9 weeks into her first pregnancy. She had not had any morning sickness.
On examination, her pulse was 100 beats per minute. She had a small uniform goitre but no tremor and no eye signs.
Investigations:
serum thyroid-stimulating hormone<0.01 mU/L (0.4-5.0)
serum free T442.0 pmol/L (10.0-22.0)
serum free T315.0 pmol/L (3.0-7.0)
anti-thyroid-stimulating hormone receptor
antibodies14 U/L (<7)
The decision was taken to treat her Graves' disease with propylthiouracil (PTU) rather than carbimazole.
What is the reason for this decision?
- A. PTU is less associated with agranulocytosis
- B. PTU is less associated with hepatitis
- C. concordance with PTU is greater
- D. PTU does not cross the placenta
- E. PTU is less associated with aplasia cutis
正解:E 🗳️
A 26-year-old woman was urgently referred to clinic with a 6-week history of retroorbital headaches and deteriorating vision. Her past medical history was unremarkable, although on questioning she admitted that she had recently found it increasingly difficult to cope with her busy job.
On examination, her pulse was 60 beats per minute and regular, and her blood pressure was 110/75 mmHg lying and 90/60 mmHg standing. She was pale and had dry skin. Visual acuities were reduced (6/12 right; 6/24 left), and she had a bitemporal inferior quadrantanopia.
Investigations:
serum sodium132 mmol/L (137-144) serum potassium4.0 mmol/L (3.5-4.9)
short tetracosactide Synacthen@ test (250 micrograms): serum cortisol (30 min after tetracosactide)185 nmol/L (>550)
plasma follicle-stimulating hormone2.7 U/L plasma luteinising hormone3.5 U/L serum prolactin1050 mU/L (<360) serum thyroid-stimulating hormone0.3 mU/L (0.4-5.0) serum free T48.0 pmol/L (10.0-22.0)
serum insulin-like growth factor 14.7 nmol/L (7.5-37.3)
MR scan of brainsee image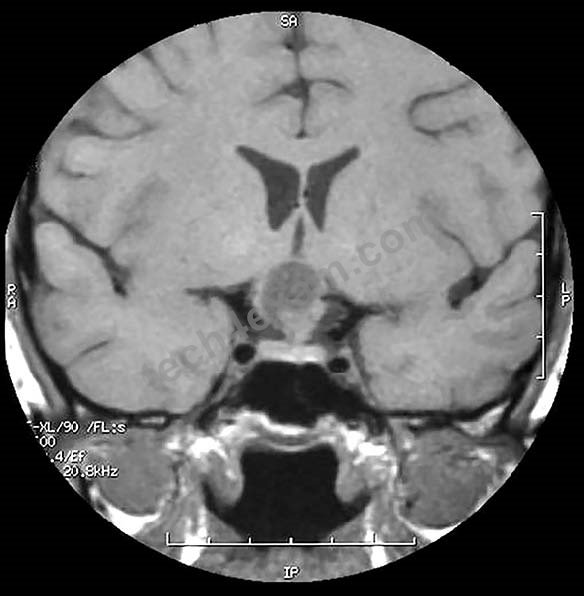
What is the most likely diagnosis?
- A. non-functioning pituitary adenoma
- B. prolactinoma
- C. Rathke's cleft cyst
- D. autoimmune hypophysitis
- E. craniopharyngioma
正解:E 🗳️
A 16-year-old girl presented with primary amenorrhoea. In early childhood she had undergone an inguinal herniorrhaphy. She had no other medical history of note. There was a family history of infertility affecting a maternal aunt.
On examination, she had adult breast development but no pubic or axillary hair. Examination was otherwise normal.
What test is most likely to aid diagnosis?
- A. plasma gonadotropins
- B. ovarian antibody titres
- C. blood karyotype
- D. ultrasound scan of pelvis
- E. MR scan of pituitary and olfactory bulbs
正解:C 🗳️
A 67-year-old woman presented to her general practitioner with a swelling in her neck. It had been present for 4-5 years and had not changed in size during that time. She was completely asymptomatic and remained well.
On examination, there was a nodular goitre and no lymphadenopathy.
Investigations:
serum thyroid-stimulating hormone1.1 mU/L (0.4-5.0)
A subsequent ultrasound scan demonstrated seven nodules bilaterally (ranging in size from 5 mm to 15 mm), which had no suspicious features.
What is the most appropriate next step in management according to British Thyroid Association 2014 Guidelines for the Management of Thyroid Cancer?
- A. subtotal thyroidectomy
- B. fine-needle aspiration of largest nodule
- C. reassure and discharge
- D. radioactive iodine
- E. levothyroxine 100 micrograms daily
正解:C 🗳️

 江藤**


